DSD-C043
Congenital adrenal hyperplasia · DSD-C043
The diagnosis of CAH, the simple-virilizing type, was made. µg/dL; >700 µg/dL suggests androgen-secreting adrenal tumors) was raised but 17-hydroxyprogesterone (17-OHP) at 55 ng/dL (<200 ng/dL excludes the diagnosis; >800 ng/dL is diagnostic, intermediate result require adrenocorticotropic hormone (ACTH) stimulation test) was low, which was against the diagnosis of CAH.
Images · 2

Case fields and evidence
- Category
-
Congenital adrenal hyperplasia
- Age
-
13-year-old
- Sex
-
Unreported
- Phenotypes
-
Hypospadias (HP:0000047); Primary amenorrhea (HP:0000786)
- Diagnosis
-
The diagnosis of CAH, the simple-virilizing type, was made. µg/dL; >700 µg/dL suggests androgen-secreting adrenal tumors) was raised but 17-hydroxyprogesterone (17-OHP) at 55 ng/dL (<200 ng/dL excludes the diagnosis; >800 ng/dL is diagnostic, intermediate result require adrenocorticotropic hormone (ACTH) stimulation test) was low, which was against the diagnosis of CAH.
- Follow-up
-
Unreported
- General phenotype
-
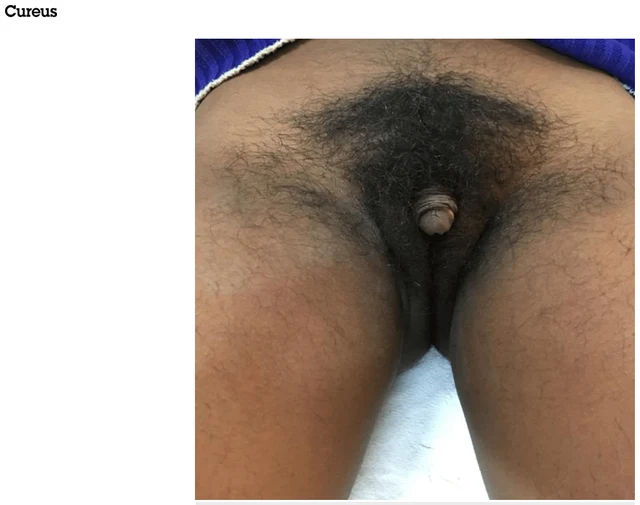
On general examination, signs of virilization were present, such as acne, frontal balding, deepening of the voice, breast atrophy (Tanner stage 2), and hirsutism. According to the modified Ferriman-Gallwey scoring system, her hirsutism score was 27, which comes under the severe category (<8 is considered mild, 8-15 as moderate, and >15 as severe) (Figure 1). To manage hirsutism, shaving, plucking, and waxing were suggested.
- Imaging
-
At that time, laboratory investigation for karyotyping was done along with an ultrasound. The CT scan showed adrenal hyperplasia (Figure 4).
- Laboratory findings
-
testosterone: 97.40 ng/dL (reference: unreported; time point: as reported in original case)
- Management
-
We prescribed tablet hydrocortisone at a dose of 10 mg in the morning and 20 mg in the evening for three months (the recommended dose is 12-18 mg/m2 daily to maintain serum 17-OHP level at 400-1,200 ng/dL).
- Pathology
-
Unreported
- Evidence level
-
See source
- Clinical history
-
See source
- Perinatal history
-
See source
- Family history
-
See source
- Growth and development
-
See source
- External genital examination
-
See source
- Puberty / Tanner
-
See source
- Karyotype
-
See source
Cite this resource
DSD Research Library | Congenital adrenal hyperplasia · DSD-C043 | v1.4.0 | 2026-11-17 | https://dsdatlas.com/en/cases/DSD-C043?version=v1.4.0