DSD-C249
46,XY DSD — disordered gonadal/androgen synthesis (17α-hydroxylase deficiency). · 46,XY · DSD-C249
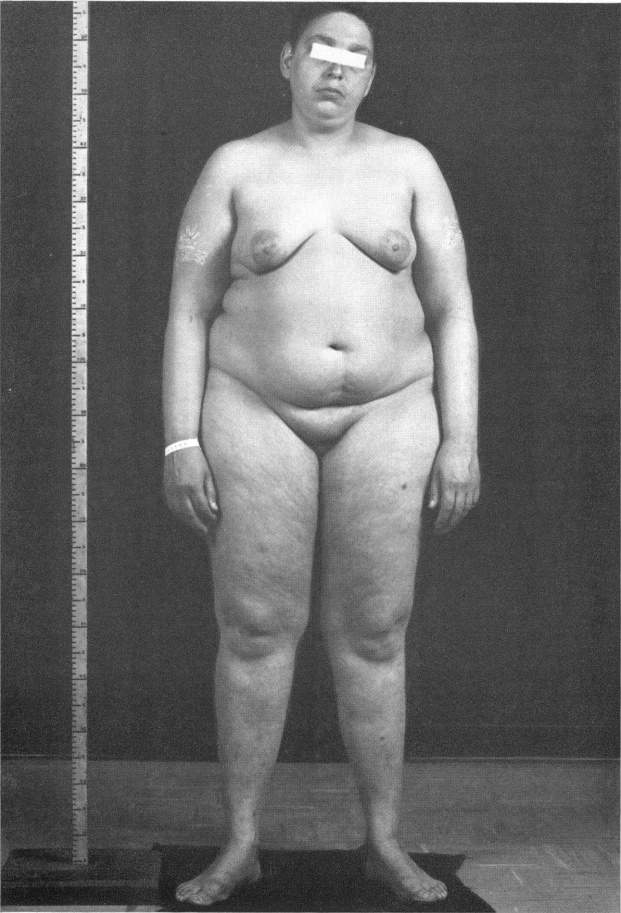
46,XY male pseudohermaphroditism, etiologically established by steroid studies as partial 17α-hydroxylase deficiency (secretion rates of corticosterone/DOC ~7–8× normal, cortisol/S/aldosterone very low).
Images · 1
Case fields and evidence
- Category
-
46,XY DSD — disordered gonadal/androgen synthesis (17α-hydroxylase deficiency).
- Age
-
24 years (at presentation; diagnosed male pseudohermaphroditism at 20 months; marked gynecomastia since age 16).
- Sex
-
Rearing sex male (ambiguous genitalia at birth; assigned male at 20 months and raised as male).
- Karyotype
-
46,XY
- Phenotypes
-
Micropenis (HP:0000054); Ambiguous genitalia (HP:0000062); Hypospadias (HP:0000047); Cryptorchidism (HP:0000028); Gynecomastia (HP:0000771)
- Diagnosis
-
46,XY male pseudohermaphroditism, etiologically established by steroid studies as partial 17α-hydroxylase deficiency (secretion rates of corticosterone/DOC ~7–8× normal, cortisol/S/aldosterone very low).
- Follow-up
-
Off-testosterone 17-KS rose; long-term testosterone maintenance with good virilization.
- General phenotype
-
Eunuchoid habitus, no temporal hair recession, smooth skin, no acne/seborrhea; high-pitched voice; marked gynecomastia, absence of virilization; no severe hypertension or hypokalemia.
- Imaging
-
IVP showed unusual bladder neck; retrograde/voiding cystogram showed irregular distal urethra and bulbous mid-urethral dilation; wrist film showed epiphyseal fusion (without changes attributable to androgen/estrogen deficiency).
- Laboratory findings
-
Low urinary 17-KS and 17-OHCS unresponsive to ACTH; plasma testosterone persistently in female range (no rise with ACTH/hCG/dexamethasone); plasma DHEA below normal; markedly elevated gonadotropins (FSH 106, LH 364 mIU/ml); very low plasma renin (0.1 ng/ml/h) and low aldosterone; aldosterone rose acutely after ACTH.
- Management
-
Infancy methyltestosterone orally + testosterone ointment increased phallic length (2.5→3.2 cm); multiple urologic operations for hypospadias/chordee; mastectomy in teens; long-term IM testosterone enanthate/propionate with virilization within 6 weeks (deepened voice, seborrhea, pubic/facial hair, increased strength).
- Pathology
-
Testicular biopsy showed Leydig-cell hyperplasia and early spermatogenesis; breast biopsy showed ducts and acini; vaginal-wall biopsy showed stratified squamous epithelium; removed testes showed tubules lined almost entirely by Sertoli cells with relative Leydig-cell increase.
- Clinical history
-
See source
- Perinatal history
-
See source
- Family history
-
See source
- Growth and development
-
See source
- External genital examination
-
See source
- Puberty / Tanner
-
See source
- Genetics
-
See source
Cite this resource
DSD Research Library | 46,XY DSD — disordered gonadal/androgen synthesis (17α-hydroxylase deficiency). · 46,XY · DSD-C249 | v1.4.0 | 2026-11-17 | https://dsdatlas.com/en/cases/DSD-C249?version=v1.4.0