DSD-C273
46,XX DSD (steroidogenic defect; POR deficiency causing a variant of CAH; with Antley-Bixler syndrome) · 46,XX · DSD-C273
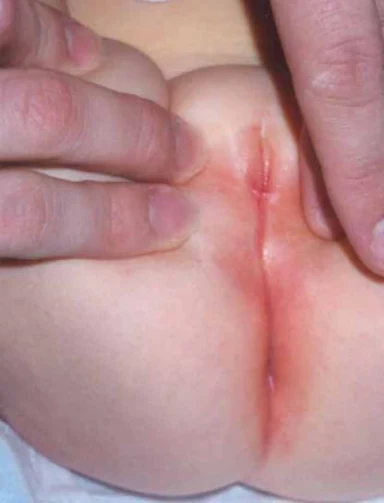
P450 oxidoreductase (POR) deficiency causing a variant of congenital adrenal hyperplasia with a mild Antley-Bixler syndrome phenotype and ambiguous genitalia (46,XX DSD).
Images · 1
Case fields and evidence
- Category
-
46,XX DSD (steroidogenic defect; POR deficiency causing a variant of CAH; with Antley-Bixler syndrome)
- Age
-
Presented in neonatal period (born at 36 weeks); last follow-up at 8 years 9 months (also described at 20 months, 4, 5, 8, 9 years)
- Sex
-
Female (46,XX), raised female, phenotypic female
- Karyotype
-
46,XX
- Genetics
-
CYP17A1, CYP21A2
- Phenotypes
-
Ambiguous genitalia (HP:0000062)
- Diagnosis
-
P450 oxidoreductase (POR) deficiency causing a variant of congenital adrenal hyperplasia with a mild Antley-Bixler syndrome phenotype and ambiguous genitalia (46,XX DSD).
- Follow-up
-
At 8y9m doing well in 3rd grade (FM auditory system); clitoromegaly resolved, labia minora still fused; cyclic vomiting syndrome diagnosed; ABS features became less distinctive with age.
- General phenotype
-
Mild ABS phenotype: brachycephaly, flat occiput, frontal bossing, mid-face hypoplasia, small mouth, dysplastic ears, depressed nasal bridge; decreased elbow extension, camptodactyly, clinodactyly; no craniosynostosis, femoral bowing or radiohumeral synostosis.
- Imaging
-
Cranial, ovarian, uterine and adrenal sonograms normal; skeletal survey at 5 weeks normal except advanced bone age (~6 months); brain MRI at 5 mo showed ventriculomegaly, corpus callosal dysgenesis and global dysmyelination, normal on repeat at 17 mo.
- Laboratory findings
-
Day-6 17-OH progesterone 1,015 ng/dl, 17-OH pregnenolone 1,496 ng/dl, total testosterone <2 ng/dl, 11-deoxycortisol 0.22 mcg/dl, DHEA 90 ng/dl (low), DHEA-S <5 (low); post-ACTH 17-OH progesterone 2,448 to 1,643 ng/dl; AM cortisol low. At 8y urinary steroids: very low androgen metabolites (androsterone, etiocholanolone), elevated pregnenolone/progesterone metabolites, reduced 17,20-lyase activity.
- Management
-
Estrogen cream for fused labia; cortisone, fludrocortisone and salt supplementation for suspected CAH, continued with elevated 17-OH progesterone; long-term low-dose fludrocortisone plus hydrocortisone replacement (stress coverage); midface advancement planned; pressure-equalization tubes, hearing aids and speech therapy.
- Pathology
-
Not reported in the original text (no biopsy; clinical, biochemical and genetic diagnosis)
- Clinical history
-
See source
- Perinatal history
-
See source
- Family history
-
See source
- Growth and development
-
See source
- External genital examination
-
See source
- Puberty / Tanner
-
See source
Cite this resource
DSD Research Library | 46,XX DSD (steroidogenic defect; POR deficiency causing a variant of CAH; with Antley-Bixler syndrome) · 46,XX · DSD-C273 | v1.4.0 | 2026-11-17 | https://dsdatlas.com/en/cases/DSD-C273?version=v1.4.0