DSD-C275
46,XY DSD (likely ovotesticular DSD or mixed gonadal dysgenesis; with gonadal germ cell tumor) · 46,XY · DSD-C275
46,XY DSD (likely ovotesticular or mixed gonadal dysgenesis) with metastatic gonadal dysgerminoma.
Images · 1
Case fields and evidence
- Category
-
46,XY DSD (likely ovotesticular DSD or mixed gonadal dysgenesis; with gonadal germ cell tumor)
- Age
-
24 years old (ambiguous genitalia at birth; bilateral breast development and phallic enlargement at age 10; cyclic hematuria at age 12; presented at 24 with abdominal pain and mass)
- Sex
-
Raised male (male social sex); predominantly male phenotype
- Karyotype
-
46,XY
- Phenotypes
-
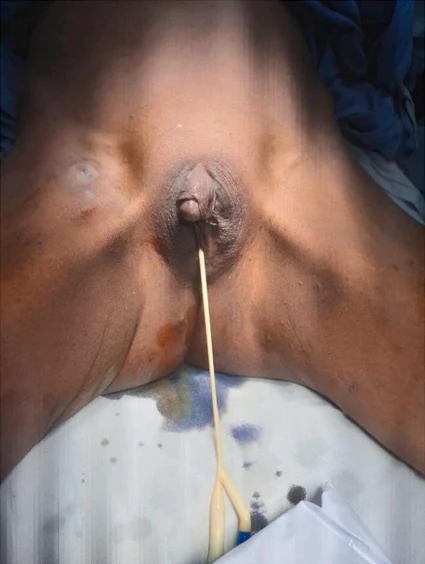
Micropenis (HP:0000054); Ambiguous genitalia (HP:0000062); Gynecomastia (HP:0000771)
- Diagnosis
-
46,XY DSD (likely ovotesticular or mixed gonadal dysgenesis) with metastatic gonadal dysgerminoma.
- Follow-up
-
Postoperative course uneventful; planned at least 2 more chemo cycles then genital reconstructive surgery; no long-term follow-up outcome provided.
- General phenotype
-
Predominantly male phenotype with ambiguous genitalia, bilateral gynecomastia and cyclic hematuria; large mobile abdominopelvic mass.
- Imaging
-
MRI showed uterus and two well-defined abdominopelvic masses (14.4x8.5 cm and 15x9 cm), likely gonadal origin by vasculature; PET-CT showed FDG-avid lymph nodes in abdomen, mediastinum, neck, left axilla, diaphragm and bilateral lung lesions; genitogram inconclusive.
- Laboratory findings
-
Low testosterone, DHEAS and AMH; LH, FSH and estradiol (E2 75.9) within normal limits; beta-HCG, CA19-9, AFP, CEA normal but CA125 (128.6) and LDH (600) elevated; LH surge during admission followed by hematuria.
- Management
-
Psychological evaluation; patient wished to remain male. Neoadjuvant chemo (carboplatin + etoposide, EP) one cycle, then febrile neutropenia, AKI (tumor lysis syndrome); later laparotomy for pain/fever: resection of bilateral adnexal masses (twisted necrotic left 15x11x8 cm, right 10x6x4 cm), subtotal hysterectomy (cervix 2-3 cm retained), omentectomy, adhesiolysis.
- Pathology
-
US-guided FNAC: tumor cells with vesicular chromatin, prominent nucleoli, tigroid background; admixed sarcoid-like granulomas, lymphocytes, occasional multinucleated giant cells; IHC SALL4 and OCT4 positive, CD30 and AFP negative, consistent with dysgerminoma. Laparotomy specimen: bilateral adnexal large necrotic/hemorrhagic/calcified masses, no viable tumor or normal ovarian cortex; uterus 4x3x1 cm with proliferative endometrium, normal tubes.
- Clinical history
-
See source
- Perinatal history
-
See source
- Family history
-
See source
- Growth and development
-
See source
- External genital examination
-
See source
- Puberty / Tanner
-
See source
- Genetics
-
See source
Cite this resource
DSD Research Library | 46,XY DSD (likely ovotesticular DSD or mixed gonadal dysgenesis; with gonadal germ cell tumor) · 46,XY · DSD-C275 | v1.4.0 | 2026-11-17 | https://dsdatlas.com/en/cases/DSD-C275?version=v1.4.0