 1 Images
Other / unclassified DSD · 46,XY · DSD-C076
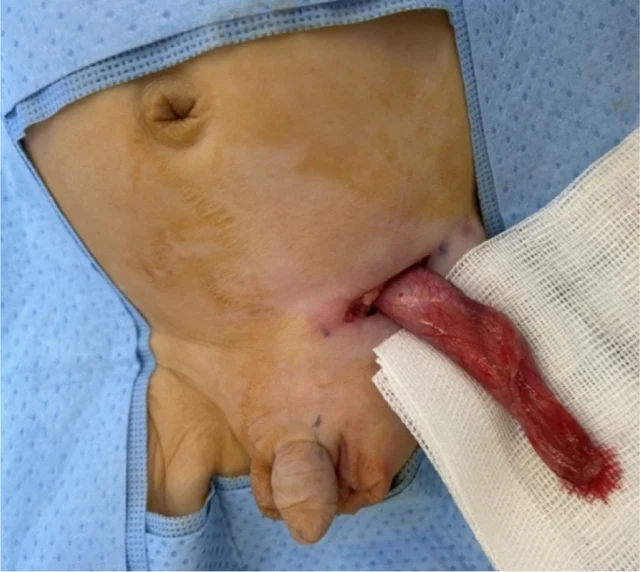
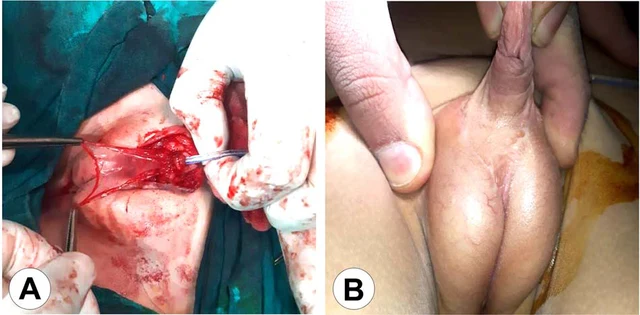
Transverse testicular ectopia as a presentation of persistent M?llerian duct syndrome associated with AMHR2 mutation(s), plus transposition of the great arteries.
Browse cases and figures from the original collection. Search by condition, gene, karyotype or phenotype and follow the source publication.
280 Image cases571 Images
Current selection: 280 Image cases · 571 Images
Select an image to enlarge it. Original images retain the complete source file.
1 ImagesTransverse testicular ectopia as a presentation of persistent M?llerian duct syndrome associated with AMHR2 mutation(s), plus transposition of the great arteries.
 1 Images
Ambiguous genitalia/DSD with left ovarian dysgerminoma.
 1 Images
45,X/46,XY mosaicism with likely co-existing complete androgen insensitivity syndrome (CAIS).
 1 Images
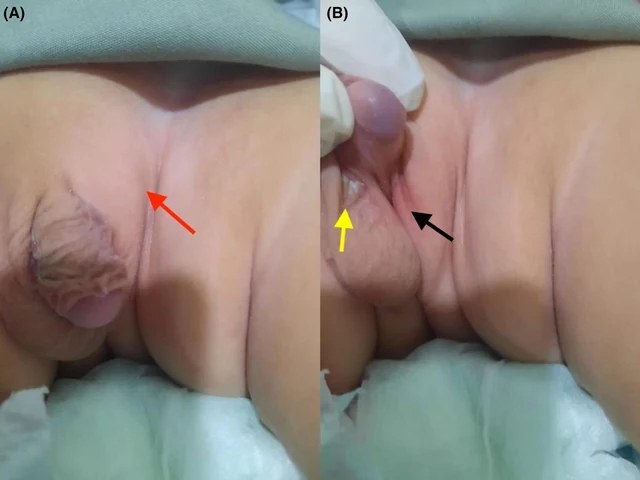
Coexistence of Jacobs syndrome and congenital adrenal hyperplasia presenting with ambiguous genitalia.
 1 Images
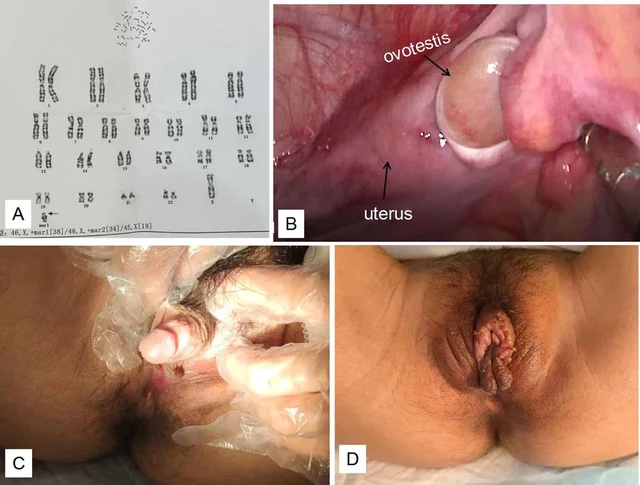
Bilateral ovotesticular DSD pathologically confirmed, with a sex cord tumor with annular tubules (SCTAT).
 1 Images
17α-hydroxylase deficiency causing congenital adrenal hyperplasia with triple X syndrome.
 1 Images
46,XX testicular DSD with double-positive SRY and Leydig cell tumor.
 5 Images

Ovotesticular disorder of sex development with unusual karyotype.
 1 Images
Simple virilizing 21-hydroxylase deficiency congenital adrenal hyperplasia.
 1 Images
Classic congenital adrenal hyperplasia due to 21-hydroxylase deficiency, simple virilising form.
 1 Images
17α-hydroxylase deficiency associated with multiple adrenal myelolipomas and severe pseudohermaphroditism.
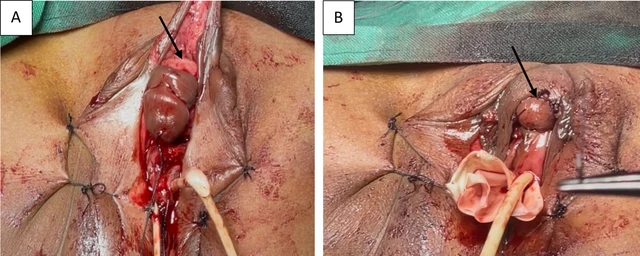 9 Images
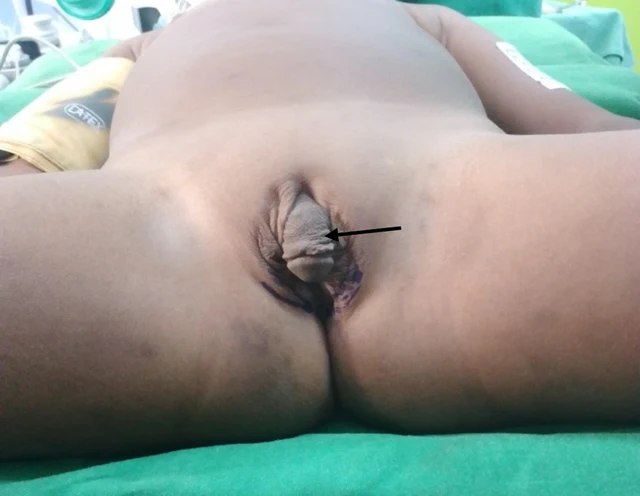
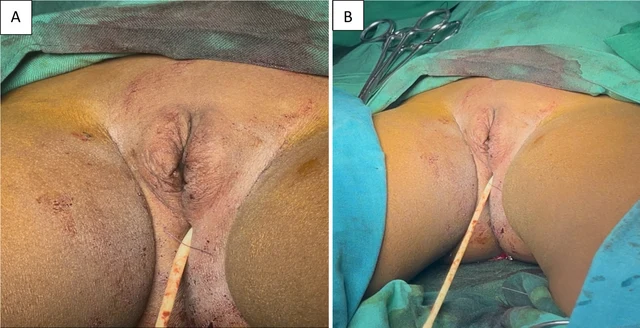
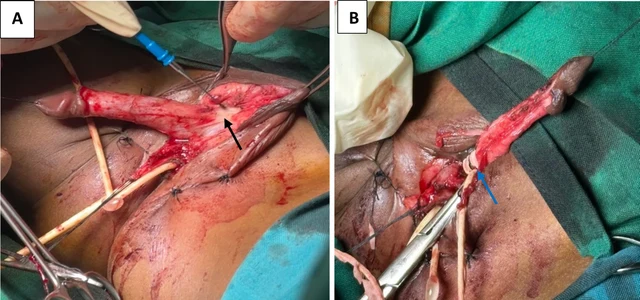
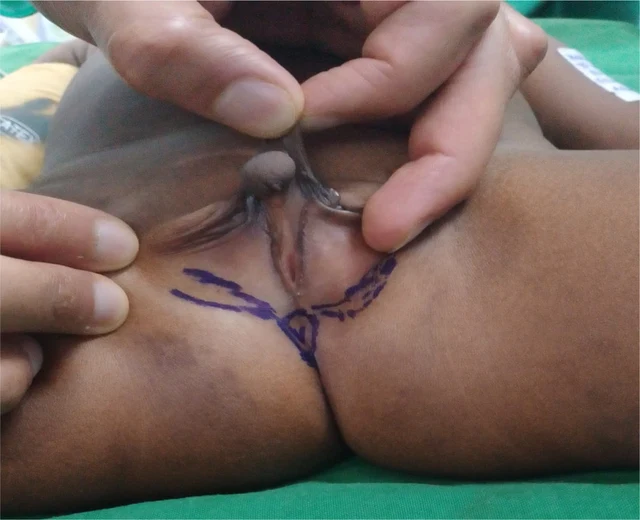

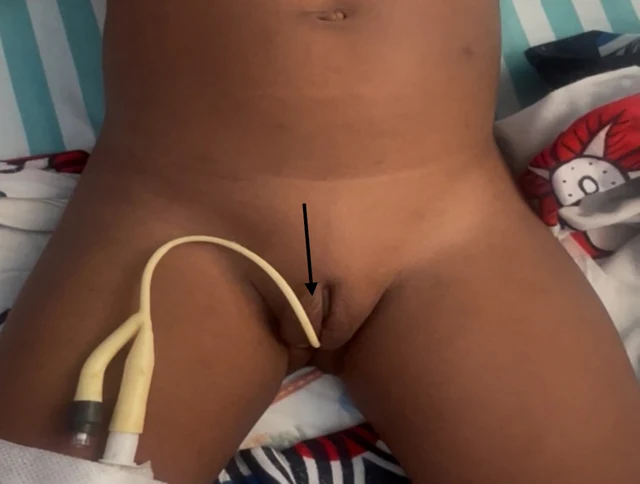
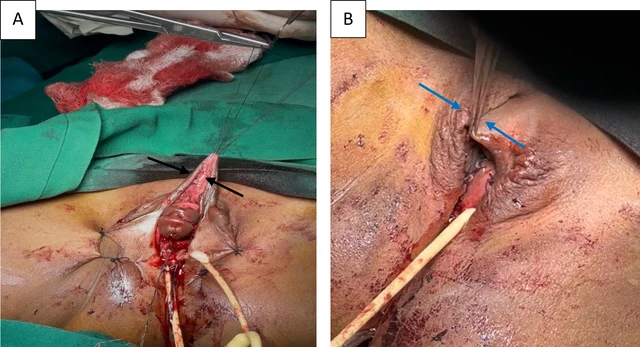
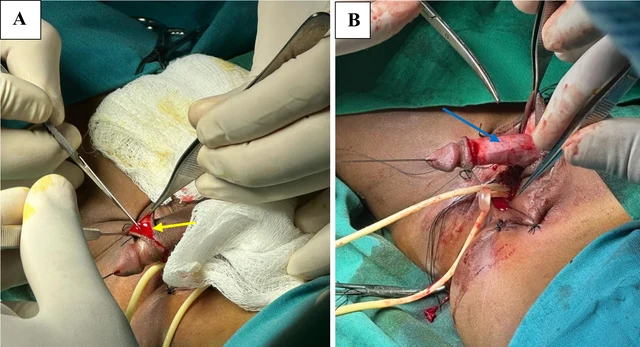
The authors clinically suspect congenital adrenal hyperplasia based on 46,XX, clitoromegaly, and mildly elevated 17-OHP; the etiology was not molecularly confirmed.
 1 Images
18 years 3 months · 46,XY DSD due to CYP17A1 defect causing 17α-hydroxylase/17,20-lyase deficiency.
 4 Images
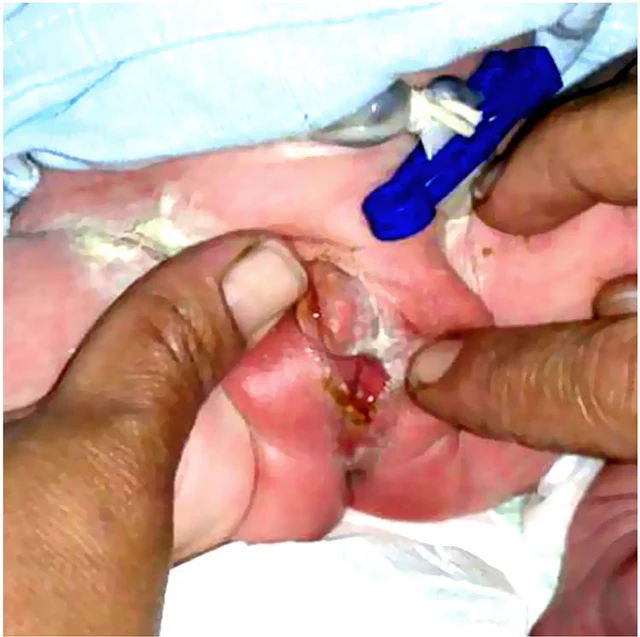
6 years · Familial partial androgen insensitivity syndrome (PAIS).
 1 Images
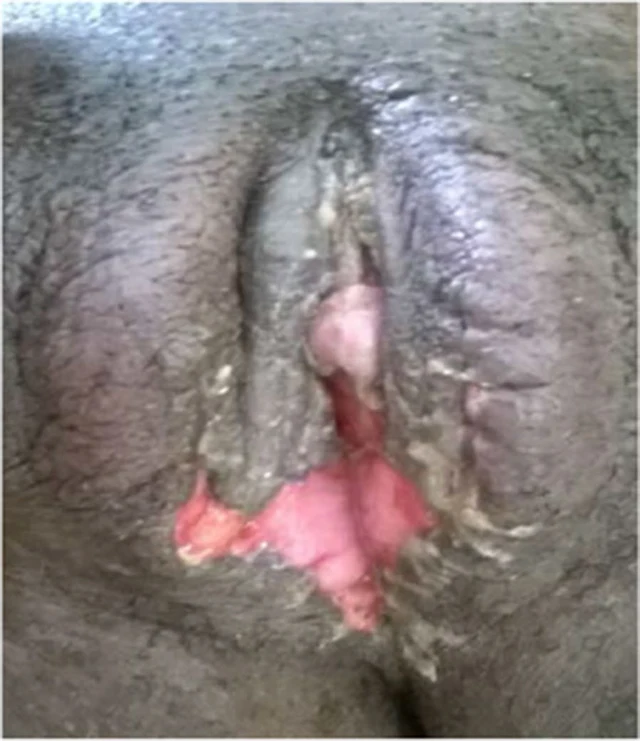
Day 1 of life · Familial partial androgen insensitivity syndrome (PAIS).
 4 Images
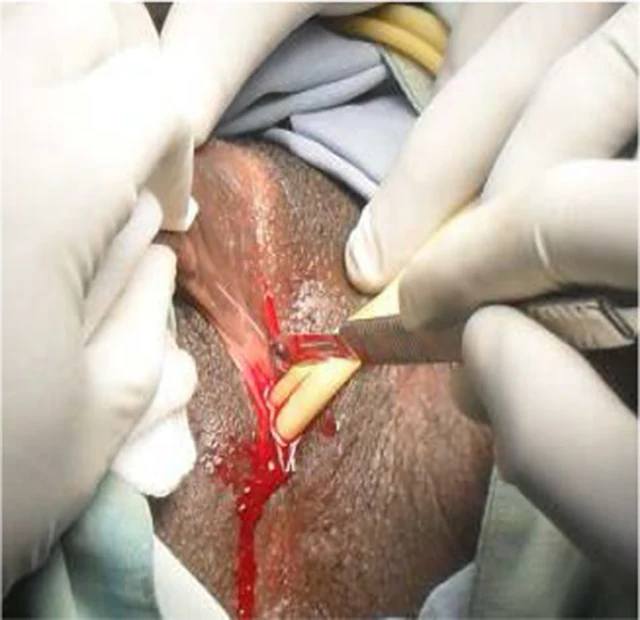
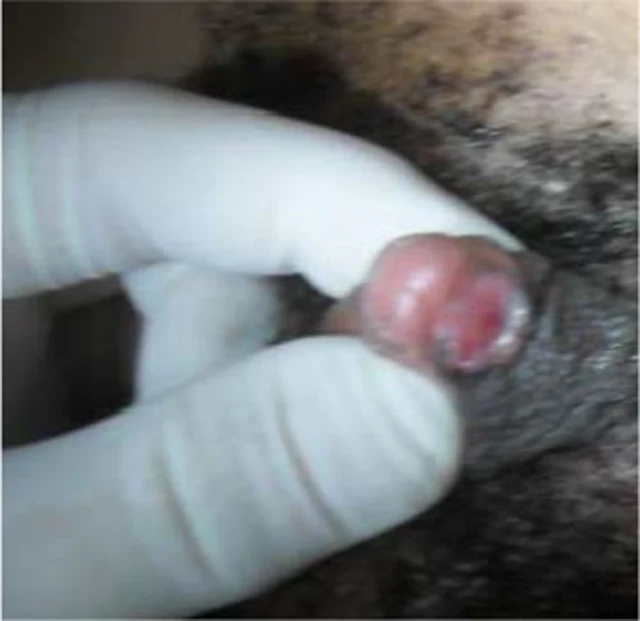
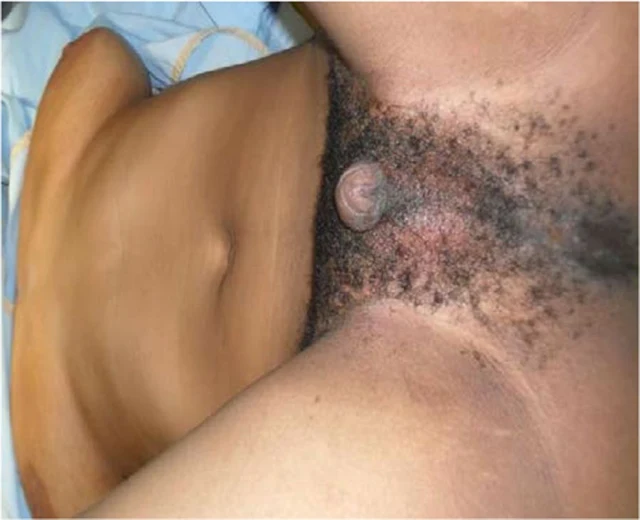
The authors termed it 46,XX DSD due to androgen excess, but provided no karyotype, hormonal, or genetic evidence; the case library lists it only as an unclassified DSD phenotype.
 1 Images
Presented at 2 years · 46,XX fetus with external genitalia virilization due to maternal androgen exposure; CAH and ovotesticular DSD excluded.
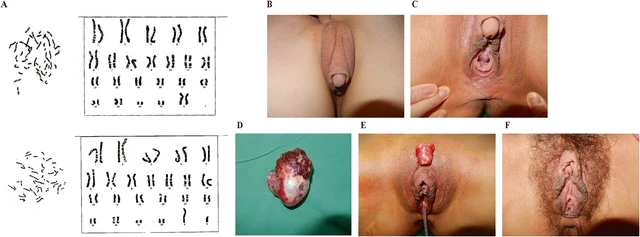 1 Images
24 years · Pathologically confirmed ovotesticular DSD with dysgerminoma within the right ovotestis.
 1 Images
Neonate; clinical photograph taken at 6 weeks · 46,XY undervirilization, which the authors speculate is related to transient disruption of androgen synthesis and/or action from prolonged high-dose nystatin combination exposure during pregnancy.
 2 Images
Presented at 24 years; surgery at 25 years · Simple virilizing congenital adrenal hyperplasia, clinically considered 21-hydroxylase deficiency.
 1 Images
6 months · 46,XY DSD due to 5α-reductase type 2 deficiency.
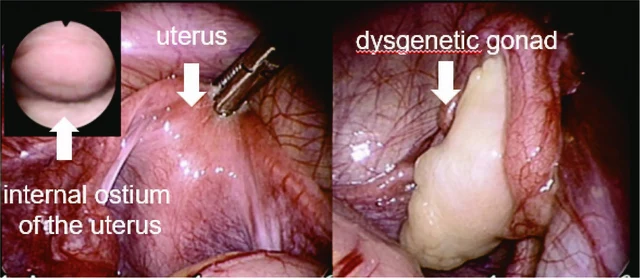 2 Images
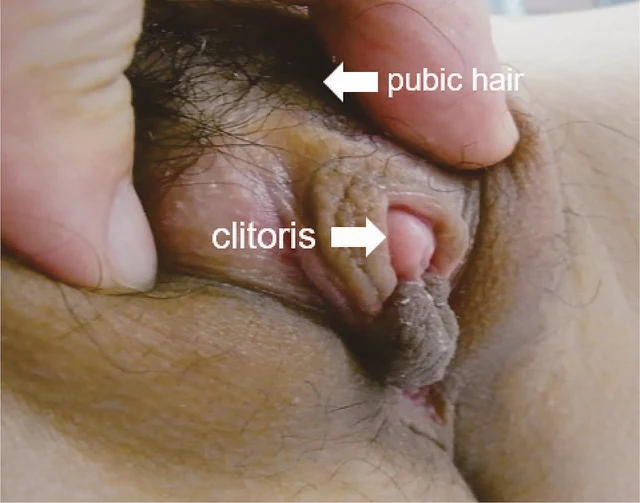
6 years 10 months · Y-chromosome-related 46,XY gonadal dysgenesis, with bilateral gonadoblastoma and suspected SOX9 regulatory-region abnormality / campomelic dysplasia spectrum.
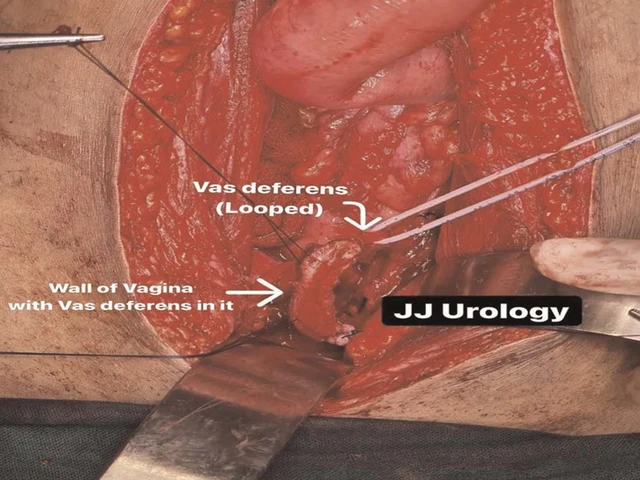 2 Images
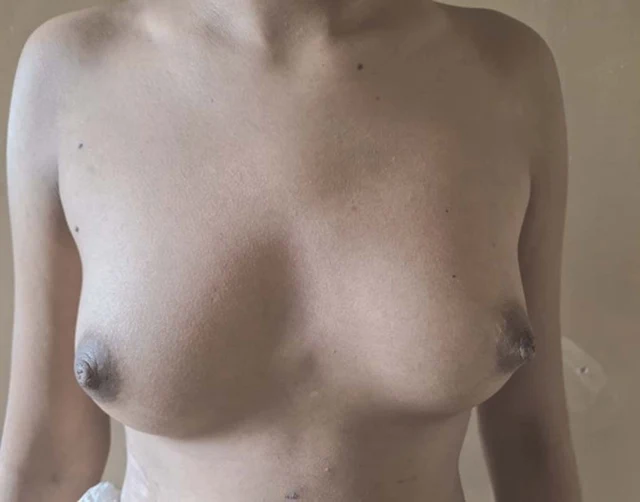
19 years · Reported by the authors as ovotesticular DSD (formerly true hermaphroditism).
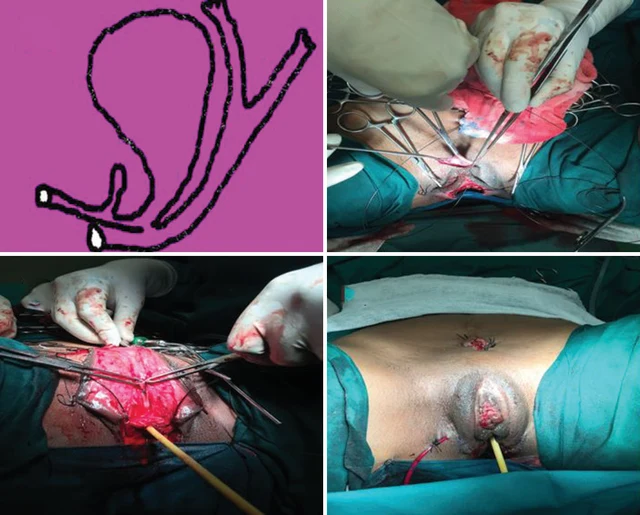 2 Images
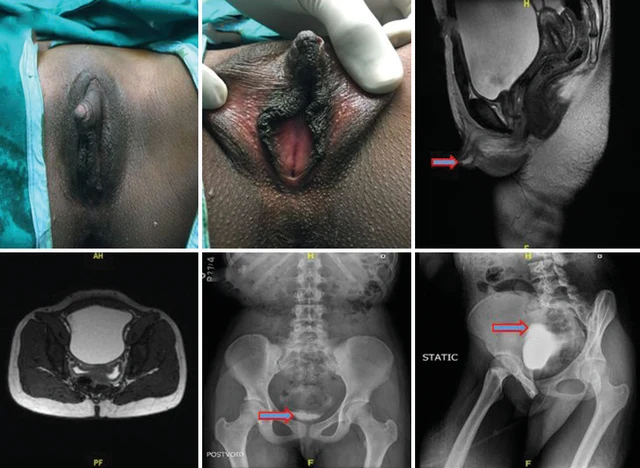
24 years · Congenital urogenital sinus anomaly with atypical external genitalia; CAH excluded by hormone testing.